In Simple Words
By converting human-led instruction into digital web modules supervised by a small centralized team, the fixed setup costs are spread over thousands of users. This dramatically drops the price per student, making the health benefits gained far outweigh the money spent to deliver the software.
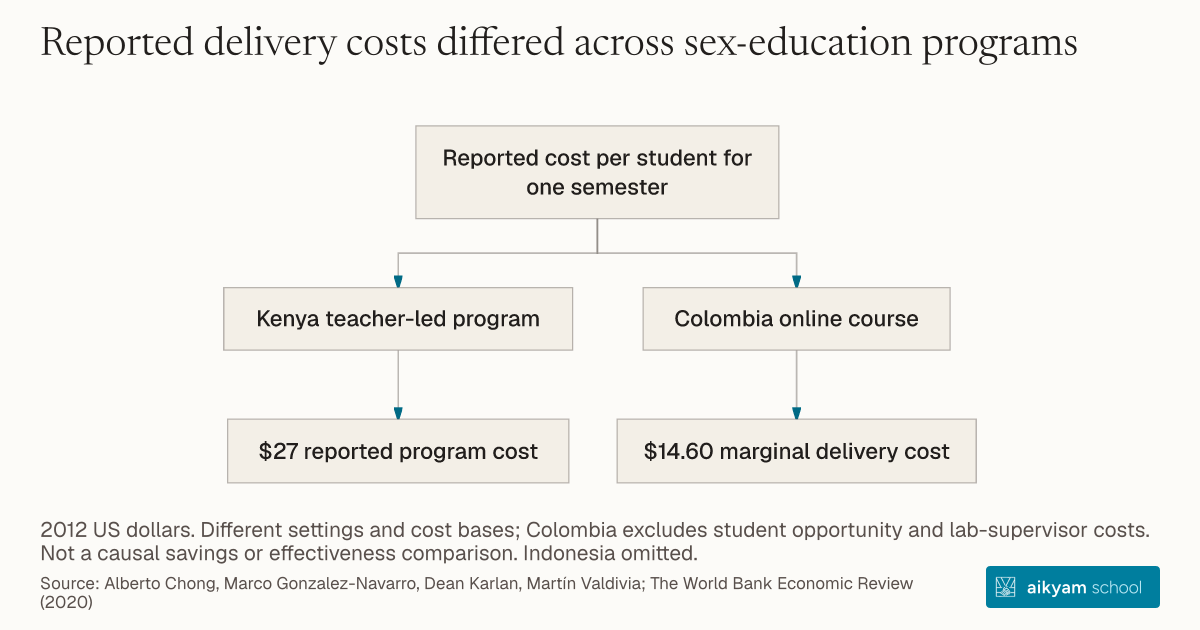
Reported cost per student for one semester
- Kenya teacher-led program
- $27 reported program cost
- Colombia online course
- $14.60 marginal delivery cost
2012 US dollars. Different settings and cost bases; Colombia excludes student opportunity and lab-supervisor costs. Not a causal savings or effectiveness comparison. Indonesia omitted.
See source →Research question
Standard face-to-face sexual health interventions in low- and middle-income countries incur high per-student costs (ranging from $27 to $85), limiting widespread government adoption and public funding sustainability.
Participants
Economic modeling based on N = 4,599 public school ninth-grade students across 21 Colombian cities.
Study Design
Cost-effectiveness and cost-benefit framework calculating marginal delivery costs against Disability-Adjusted Life Years (DALYs) saved from prevented sexually transmitted infections.
Results
Marginal course delivery cost was $14.60 per student ($10 remote tutor, $2.10 platform, $2.50 hardware depreciation); $1,000 spent averts 2.20 STIs, yielding a cost per averted STI of $455 against a monetary benefit of $785 per averted STI (Benefit-to-Cost Ratio = 1.72).
Takeaway
Reallocate public health budgets toward centralized digital learning platforms to lower per-capita costs and achieve benefit-to-cost ratios exceeding 1.5 in adolescent health programs.